Author: Inirra

Inirra is the health editorial desk of PT INIRRA NAYA MANDIRI, the publisher of NayaBisa. Articles under this byline are researched against published clinical and public-health sources – including PubMed, NHS, WHO and ACOG – and checked for accuracy before publication.

  • The 4 Menstrual Cycle Phases, Explained Simply

    The 4 Menstrual Cycle Phases, Explained Simply

    School biology draws the cycle as a tidy circle divided into labelled segments, and real life rarely cooperates. Cycles drift, stretch and sometimes skip altogether. Understanding what each of the four menstrual cycle phases is doing makes those changes easier to read, and it makes the loose timing less alarming. The count starts on day 1, the first day of bleeding, and runs until the day before the next period begins.

    Key takeaways

    • Day 1 is the first day of real bleeding, so a cycle is counted from bleed to the day before the next bleed.
    • Anything from 21 to 35 days is treated as normal by the NHS, while the US Office on Women’s Health calls 24 to 38 days regular.
    • Ovulation is better pinned to the next period, about 14 days before it starts, than to day 14 of the current cycle.
    • The luteal phase is the steady part at roughly 12 days, while the follicular phase is the one that stretches or shrinks.
    • Patterns across the four menstrual cycle phases are easier to see after two or three logged cycles than on any single day.

    How cycle days are counted

    Day 1 is the first day of proper bleeding, not the light spotting that sometimes comes before it. The cycle ends the day before the next period begins, so a 28-day cycle runs 28 days from bleed to bleed. Every phase boundary is measured against that definition.

    What counts as normal depends on who you ask. The NHS describes periods arriving anywhere from every 21 days to every 35 days, while the US Office on Women’s Health calls 24 to 38 days regular and notes that length often differs from month to month. Both are working definitions from different populations rather than one true range.

    The average of 28 days is a convenient round number, not a rule. In a study of 612,613 ovulatory cycles logged through an app, the mean was 29.3 days, and length varied from person to person. No calendar month matches the four menstrual cycle phases, so logging your own start dates for a few months tells you more than the textbook figure.

    The four menstrual cycle phases, in order

    Two hormones do most of the driving, and each of the four menstrual cycle phases is defined by what estrogen and progesterone are doing. The boundaries between them are soft, which is why two people with the same 28-day cycle can feel completely different at day 20.

    Days 1 to 5: the menses phase

    The cycle begins with bleeding because a pregnancy did not happen, so the lining built for it is no longer needed. Estrogen and progesterone fall to their lowest levels, the lining sheds, and most people bleed for three to five days, though anything from three to seven days is usually nothing to worry about. Bleeding is heaviest on the first two days and lightens after that. If your periods produce large clots or soak through protection quickly, our guide to period blood clots explains where the line sits.

    The follicular phase: rebuilding the lining

    This stretch overlaps with your period and finishes at ovulation, which makes it the longest and least predictable part of the cycle. Estrogen climbs, follicle-stimulating hormone wakes a group of follicles in the ovaries, and by roughly days 10 to 14 one of them has produced a mature egg.

    In the 612,613-cycle study the follicular phase averaged 16.9 days but ranged from 10 to 30. Because the second half of the cycle stays fairly fixed, a late period is usually a late ovulation. Rising estrogen is also why energy tends to come back around this point, the idea behind training with the follicular phase.

    Ovulation: the egg leaves

    Around the midpoint, a surge of luteinizing hormone makes the ovary release its egg, and that is ovulation. In a textbook 28-day cycle it lands near day 14, which is where the famous number comes from. Clinically it is better anchored to the period that follows, since the NHS says ovulation pain typically shows up about 14 days before a period.

    The egg survives roughly 12 to 24 hours, while sperm can live in the uterus for three to five days, so the days before ovulation are the ones that count for conception. The signs are subtle, and tracking them without an app is possible but takes practice.

    The luteal phase: the steady stretch

    After the egg is released, the empty follicle becomes the corpus luteum and starts producing progesterone. That hormone keeps the uterine lining thick and calm in case a fertilised egg implants. If it does not, both hormones drop, the lining comes away, and the next cycle begins. This stage is the most consistent of the four menstrual cycle phases: in the same large study it averaged 12.4 days, with a range of 7 to 17.

    What the phases usually feel like

    Articles about the four menstrual cycle phases often describe them as four moods, running from motivated to miserable. Diary studies support something smaller and more individual. In one prospective study, 22 naturally cycling participants and 18 pill users logged symptoms and gave daily saliva samples for 28 days. Hormone levels did track with energy, agitation and feelings of attractiveness, and progesterone showed the largest effect, but 22 people is a thin sample to generalise from.

    Premenstrual symptoms are common and well documented. The Office on Women’s Health lists cramping, headaches, moodiness, forgetfulness, bloating and breast tenderness, all of which tend to build before bleeding starts and ease once it does. Asthma and irritable bowel symptoms can shift with the cycle too, so a rough week is not automatically hormonal. There is more in our Cycle & Fertility archive if you want to go deeper.

    Keeping your own record beats trusting a chart. Note your bleeding days, energy and mood for two or three cycles and the pattern will surface on its own, including the stretch where you need more rest. If you want to eat around the cycle, our phase-by-phase food guide covers what tends to help at each stage.

    When to see a doctor

    NHS guidance separates what can wait from what should be checked. Bleeding between periods, bleeding after sex, or any bleeding after menopause should be looked at by a doctor, and so should a cycle that has changed and stayed changed. See a GP if you have missed three periods in a row and a pregnancy test is negative. Severe pain or bleeding that makes you miss work or school is treatable, so raise it rather than push through it.

    How Lail can help

    Lail is our own period tracker for Android, built around one idea: your data stays on your phone, with no account and no cloud sync. You can log bleeding, symptoms, mood and weight, then watch your own phases line up over a few months instead of comparing yourself to a diagram. Premium adds a PDF export that is genuinely useful to bring to an appointment. Lail is on Google Play, and the rest of our apps are listed on the products page.

    Is ovulation always on day 14?

    No. Day 14 is the average for a 28-day cycle and nothing more. Ovulation is better estimated as about 14 days before the next period, which is why the date slides when a cycle runs longer or shorter.

    Which phase leaves you most tired?

    The last days of the luteal phase and the first days of bleeding are when energy usually dips, because estrogen and progesterone are both falling. That pattern is common, but the four menstrual cycle phases do not come with fixed moods. If tiredness is severe or comes with heavy bleeding, ask a doctor about checking your iron levels.

    How long should a period last?

    Two to seven days, with about five being typical, according to the NHS. Total blood loss usually falls between 20 and 90 ml, and bleeding is heaviest on the first two days. If your periods have been getting longer or heavier than your normal, that is worth a conversation with a GP.

    Can I use a tracking app to avoid pregnancy?

    Do not rely on it. An analysis of 543,167 cycles found calendar-based tracking flagged at least one fertile day as safe in 67% of cycles, with an estimated pregnancy risk of 22%. If you are trying to avoid pregnancy, use a method with proper evidence behind it.

    This article is educational and does not replace advice from a qualified healthcare professional. If something about your cycle worries you, talk to a doctor.

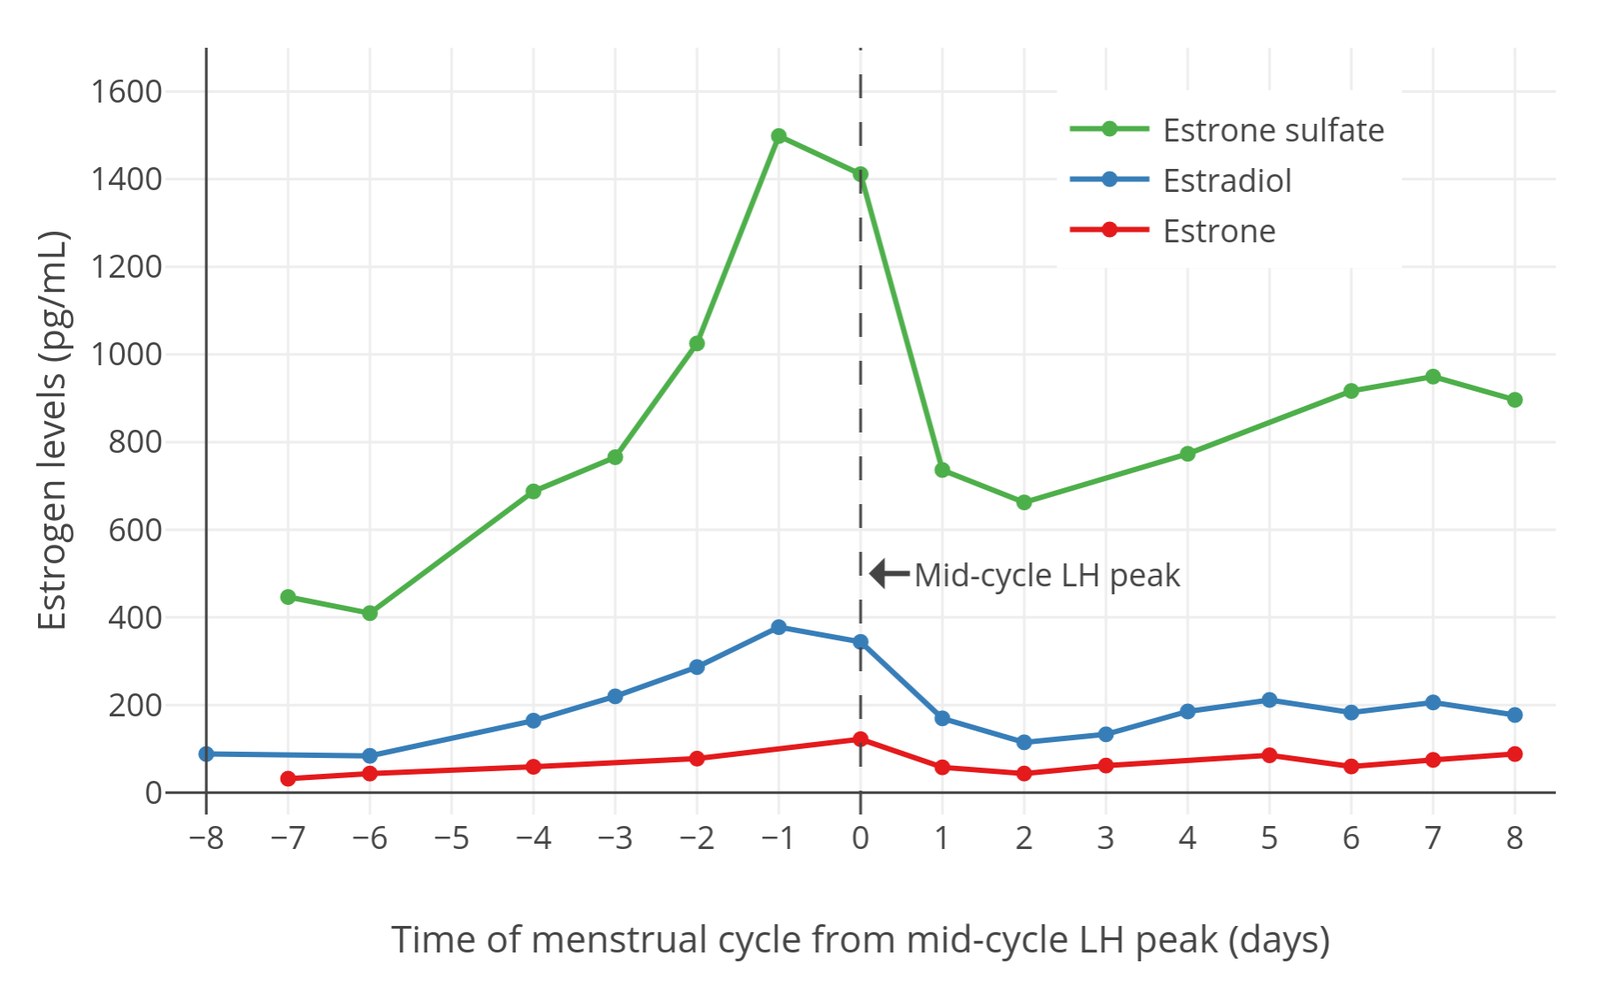
    Featured image: estradiol, estrone and estrone sulfate levels across the normal human menstrual cycle, by Medgirl131 via Wikimedia Commons, licensed under CC BY-SA 4.0.

    Sources

  • Period Blood Clots: What’s Normal and When to Ask

    Period Blood Clots: What’s Normal and When to Ask

    There is a moment in most cycles when what lands on the pad stops looking like a liquid and starts looking like something solid. Nobody explains it in advance, so it is easy to jump to the worst conclusion. Period blood clots are a normal part of a heavy flow, and the useful questions are how big they get and how often they appear. Knowing that turns a frightening sight into something you can measure.

    Key takeaways

    • Clots form when the flow is fast enough that the uterus cannot dissolve the fibrin mesh inside the blood.
    • Small clots on your heaviest days are common and are not a problem in themselves.
    • Period blood clots the size of a quarter or larger, more than once or twice a day, are one of the standard signs of heavy menstrual bleeding.
    • Heavy bleeding is worth investigating mainly because it can slowly drain your iron stores.
    • What feels like a very heavy period does not always match what gets measured, so track the details rather than the feeling.

    What period blood clots actually are

    Blood from a cut turns into a gel because fibrin forms a mesh through it. Menstrual blood usually does not, since the lining of the uterus is full of enzymes that dissolve that mesh as fast as it forms. When the flow is heavy, the dissolving system cannot keep up and some blood arrives already clotted.

    At the same time, the uterus is working to stop the bleeding. Platelets clump at the exposed vessels, fibrin is deposited, and the muscle of the womb contracts to squeeze those vessels shut. A 2026 review of menstrual haemostasis notes that the flow conditions at the tiny spiral arteries which bleed during a period have never been measured directly, so the balance is still described in models.

    One piece of this has been tested. Women with heavy bleeding do not break down clots faster in their bloodstream, which is why heavy periods are treated as a local problem in the endometrium rather than a clotting disorder.

    What a normal amount of clotting looks like

    The heaviest days are the ones that produce clots. NHS guidance describes a typical period as lasting 2 to 7 days, usually about 5, with the flow heaviest in the first 2 days and a total loss of roughly 20 to 90ml, or about 1 to 5 tablespoons.

    The size thresholds used by clinicians all point the same way. NHS guidance flags clots larger than about 2.5cm, the size of a 10p coin, as one sign of heavy periods. The American College of Obstetricians and Gynecologists describes menstrual flow with blood clots as big as a quarter or larger. Cleveland Clinic lists clots the size of a quarter or bigger more than once or twice as a sign of heavy menstrual bleeding.

    The size of your period blood clots is the detail worth noticing, more than their colour or texture. Smaller clots, appearing once or twice on your heaviest day, do not feature on any of those lists.

    When period blood clots are worth checking

    Period blood clots are a sign to act on when they come with a flow that disrupts your life. Any of these patterns is worth an appointment:

    • Soaking through a pad or tampon every hour for several hours in a row.
    • Needing a pad and a tampon together, or changing a pad every 1 to 2 hours.
    • Bleeding that lasts longer than 7 days, even when the period blood clots themselves are small.
    • Bleeding through to your clothes or bedding, or avoiding plans because of your period.

    Heavy bleeding is not rare. About one third of women seek treatment for it, and Cleveland Clinic puts the share of people who menstruate affected by it between 27% and 54%.

    What matters is the blood loss rather than the clotting itself. Losing more blood than your body replaces can drain your iron stores and lead to iron deficiency anaemia, which shows up as tiredness, shortness of breath and a faster heartbeat. Feeling weak and dizzy during your period is often the first visible sign of that iron dip. Avoiding exercise during your period is itself on the NHS list of signs, so putting your training on hold is a symptom rather than a solution.

    What can cause larger clots

    Most large clots are the visible end of a heavy flow. Fibroids, adenomyosis, endometriosis and polycystic ovary syndrome all appear on the standard lists, along with thyroid problems and, in the first year of use, the copper intrauterine device.

    Inherited bleeding disorders are the cause that gets missed most often. Von Willebrand disease and platelet function disorders can present as nothing more than heavy periods, and a 2026 study of 235 teenage girls treated for iron deficiency anaemia found that 40.9% screened positive for von Willebrand disease after their iron levels were corrected.

    Medicines can do it too, since blood thinners and aspirin increase menstrual bleeding. Heavy periods are also common in the years approaching menopause, when cycles become less predictable.

    A small number of cases have a more serious cause. NHS guidance notes that heavy periods can rarely be a sign of womb cancer, and ACOG lists ectopic pregnancy and miscarriage among the causes.

    Why “it looks like a lot” is not the same as a lot

    How alarming your period blood clots look and how much blood you actually lose do not line up as neatly as you would expect. In a 2025 study, 79 people who described their periods as heavy had their loss measured, and the median was 66ml, with only about a quarter passing the 120ml threshold that defines heavy bleeding. Pad counts told a similar story: the heavy group used a median of 21.5 pads per cycle but still overlapped with those whose measured loss was normal.

    That cuts both ways. Some people who dread their periods are bleeding inside the normal range, while others who think theirs are manageable lose more blood than they realise. A 2026 validation study found a photo-based method matched the laboratory standard closely enough to detect heavy bleeding with 100% sensitivity and 93.5% specificity.

    How to track period blood clots before your appointment

    It helps to bring numbers rather than adjectives. ACOG advises using a calendar or a period-tracking app to record several cycles before your visit, including the dates your period started, how long the bleeding lasted and whether the flow was light, medium or heavy. Cleveland Clinic adds the details that change what happens next: cramping, any bleeding between periods and any large clots you passed.

    Three things are worth logging: the largest clot you passed, measured against a coin, the number of pad or tampon changes on your heaviest day, and how many days the bleeding lasted. If you would rather not hand your cycle history to a company, a private tracker keeps the log on your phone, which is the same information your doctor needs. There is more on cycle symptoms in our Cycle and Fertility archive.

    When to see a doctor

    Book a routine appointment if your periods have been heavy for a while, if they interfere with work, exercise or sleep, if you have severe pain, or if you bleed between periods or after sex. Post-menopausal bleeding always needs checking, and so does bleeding that is heavier than anything you have had before.

    Seek urgent care rather than waiting if you are soaking through pads very quickly, if you feel faint, dizzy or breathless, or if you have severe pain that painkillers are not touching. If you are pregnant or might be, heavy bleeding with period blood clots should be assessed urgently.

    How Lail can help

    Lail is our own period tracker, built for exactly the kind of record a doctor asks for. It logs flow, symptoms, mood and weight, and keeps everything on your phone with no account and no cloud sync. Premium adds a PDF export you can take to an appointment, and the app is free to download with ads. Lail is on the Play Store, and you can see it with the rest of our apps on our products page.

    Frequently asked questions

    Are period blood clots normal?

    Period blood clots are common, especially on your heaviest days, and a small one now and then is not a medical problem. What makes them worth checking is size and repetition rather than their presence. Clots around the size of a quarter, arriving more than once or twice a day, count as a sign of heavy menstrual bleeding.

    How big is too big for a clot?

    NHS guidance draws the line at about 2.5cm, roughly the size of a 10p coin, and ACOG uses a quarter as its comparison. Period blood clots that reach that size several times a day are worth mentioning to a doctor. One small clot on day one is a different situation entirely.

    Can large clots mean a miscarriage?

    Clots can be passed during a miscarriage, and heavy bleeding in early pregnancy is a reason to seek care the same day. That does not make every clot a sign of pregnancy loss, since fibroids, adenomyosis and plain heavy flow explain most of them. If you might be pregnant, treat large clots with pain as urgent.

    Do clots mean I have a bleeding disorder?

    Usually not, but bleeding disorders are under-diagnosed and heavy periods are often their only visible sign. Von Willebrand disease is the most common inherited one, and it turns up more often when a bleeding history is combined with a record of menstrual loss. That is one reason the clot sizes you note down are useful rather than fussy.

    This article is educational only and is not medical advice. Cycle patterns vary widely, and only a qualified healthcare provider can assess your symptoms or decide whether you need tests.

    Featured image: “SABA damebind” by Geir Ove Andreassen / Anno Kvinnemuseet, CC BY-SA 4.0, via Wikimedia Commons (https://commons.wikimedia.org/w/index.php?curid=98467535).

    Sources

  • Heartburn in Pregnancy: What Helps and What to Avoid

    Heartburn in Pregnancy: What Helps and What to Avoid

    Somewhere in the middle months, a burning ache starts turning up after dinner and gets worse the moment you lie down. It is easy to wave off as one more minor annoyance, especially when there are bigger things to ask about at your next appointment. But heartburn in pregnancy is genuinely common, and most people can improve it a lot with fairly small changes. Here is what drives it, what actually helps, and what is safe to take.

    Key takeaways

    • Estimates of how common heartburn in pregnancy is vary widely, from about 30% to 80% of pregnant women.
    • A 2025 meta-analysis of 21 studies covering 9,497 pregnant participants put the pooled prevalence of reflux symptoms at 40.96%, rising to 55.93% in the third trimester.
    • Smaller and slower meals, staying upright after eating, and leaving three hours between dinner and bed do most of the work.
    • Antacids and alginates are the usual first-line medicines, and a meta-analysis of 5,618 first-trimester PPI exposures found no significant rise in major malformations.
    • Call your midwife or GP if you cannot swallow properly, spit up blood, lose weight, or if symptoms keep waking you at night.

    Why heartburn in pregnancy gets worse over the months

    Two things happen at once, and neither is your fault. Progesterone relaxes the ring of muscle between your stomach and your food pipe, so acid slips back up more easily. Your growing uterus also pushes your stomach upward, which is why the third trimester is usually the roughest stretch.

    Digestion also slows down, so food sits in the stomach longer and brings on bloating, reflux and constipation together. You are more likely to be affected if you had heartburn before you were pregnant, or if you have been pregnant before. It also turns up alongside other third-trimester complaints such as back pain.

    The numbers back up how ordinary this is. A 2025 systematic review and meta-analysis pooled 21 studies covering 9,497 pregnant participants and put the prevalence of reflux symptoms at 40.96%. Broken down by trimester, it climbs from 26.12% in the first to 33.40% in the second and 55.93% in the third. Pregnant women in those studies were more than eight times as likely to report reflux symptoms as non-pregnant controls.

    What helps day to day

    The advice that shows up everywhere is boring and effective. Eat smaller meals more often instead of three big ones, and slow down while you eat. Sitting up straight during and after a meal takes pressure off your stomach. Leaving at least three hours between your last food and bedtime matters more than most people expect.

    Where you sleep counts too. Raising the head of your bed by 10cm to 20cm, using blocks or books under the legs, keeps acid from travelling upward overnight. Sleeping on your left side helps as well. Extra pillows do not work, and can make things worse by pressing on your belly.

    Cutting back on caffeine and on rich, spicy or fatty food eases symptoms for many people. Some people get quick comfort from yogurt, a glass of milk, or chewing gum, though that is relief rather than a cure.

    The evidence behind these habits is thinner than the confidence of the advice suggests. A BMJ Clinical Evidence overview rated the efficacy of six interventions, including acid-suppressing drugs, antacids with or without alginates, raising the head of the bed, and cutting caffeine, fatty food or meal size. Its 2015 update added no new trials at all. Treat the list as sensible clinical practice rather than proven protocol.

    If diet and habit changes have not touched your heartburn in pregnancy, that is normal. It means you have finished the first line of care, not that you failed at it.

    What is safe to take

    Two families of medicine do most of the work. Antacids neutralise the acid already sitting in your stomach, while alginates form a barrier that stops it coming back up. Both are available from a pharmacist, and you should say that you are pregnant, because some antacids are not suitable.

    One timing rule catches people out. Do not take antacids within two hours of your folic acid or iron supplement, because they stop those supplements being absorbed properly.

    If antacids and alginates are not enough, your GP can prescribe something stronger, usually a proton pump inhibitor such as omeprazole or lansoprazole. The safety picture is reassuring but not perfect. A 2023 meta-analysis pooled 11 studies covering 5,618 first-trimester PPI exposures and found no significant increase in major congenital malformations, with an odds ratio of 1.10 and a confidence interval that crossed 1.0.

    The honest caveat is that this evidence comes from observational studies, and there is not enough data to judge each PPI on its own. Cleveland Clinic makes a related point from the other direction: most drug safety trials exclude pregnant women, so more is unknown than anyone would like. Ask your own provider before starting anything, especially in the first trimester.

    What to skip

    • Do not stack extra pillows to lift your head, use blocks under the bed legs instead.
    • Do not eat within three hours of going to bed, or lie down straight after a meal.
    • Do not wear anything tight around your waist.
    • Do not smoke or drink alcohol, because both make reflux worse and both harm the baby.

    Smoking deserves its own line because it works directly on the problem. Chemicals in cigarette smoke relax the ring of muscle at the lower end of your gullet, the same mechanism that lets acid travel back up. It also raises the risk of premature birth and low birthweight, so ask your midwife for help stopping.

    Several folk remedies for heartburn in pregnancy sound harmless and are simply unproven. There is no good evidence behind them. Stick with the habits and the pharmacy shelf.

    Do not stop a prescribed medicine on your own because you think it is worsening your reflux. Speak to your GP, who may be able to switch you to something else.

    Does heartburn mean a hairier baby?

    This one has been passed down for generations, and researchers actually tested it in 2006. They asked 64 pregnant women to rate how severe their heartburn was, then had independent coders score newborn hair volume from photographs taken shortly after birth. Severity and hair volume were correlated, at r = 0.40.

    The split was striking enough to publish. Of the 28 women with moderate or severe heartburn, 23 had babies with average or above-average hair. Of the 12 women with no heartburn, 10 had babies with less hair than average or none at all. The authors proposed that pregnancy hormones might relax the oesophageal sphincter and influence fetal hair growth at the same time.

    Read that as a curiosity, not a forecast. Sixty-four women in a single 2006 study is a small sample, and nobody has repeated it since. Symptom severity was also unrelated to the baby’s sex, so a hairy baby and a girl are not linked either.

    When to get medical help

    Routine reflux is uncomfortable, not dangerous, and the list of things that should prompt a call is short. See your midwife or GP if lifestyle changes and pharmacy medicines are not controlling your symptoms, or if heartburn is happening most days.

    NHS guidance also lists difficulty swallowing, a hoarse voice, a cough that keeps coming back, swollen glands on each side of your neck, unexplained weight loss, and pain or swelling in your stomach as reasons to get checked. Cleveland Clinic adds heartburn that wakes you at night, spitting up blood, and black stool.

    One warning is worth knowing by heart. Heartburn can feel like a heart attack. If you have never had it before and you are having chest pain, contact your provider or go to the nearest emergency room instead of waiting to see whether it settles. More symptom guides are collected in the pregnancy health archive.

    How Utun can help

    Utun is our own pregnancy companion app, built for exactly this stretch of pregnancy. It gives you development information with daily guidance matched to how far along you are, plus a weight log, a kick counter, a contraction timer, a mood journal, a hospital bag checklist and trimester to-do lists. If you want one place to keep track of symptoms like these, it is on Google Play and listed with our other apps on the products page.

    Is heartburn in pregnancy a sign of a girl?

    No. In the 2006 study that measured it, symptom severity was unrelated to fetal sex, along with parity, age and weight. The sex prediction belongs with the other old wives’ tales about carrying high or craving sweets.

    Can I take omeprazole while pregnant?

    Possibly, but only with a doctor’s agreement. NHS guidance says a GP may prescribe a proton pump inhibitor if antacids and alginates have not worked. The pooled evidence from 5,618 first-trimester exposures found no significant increase in major malformations, but it came from observational studies, so it is not a green light to self-prescribe.

    Why is heartburn worse at night?

    Lying flat takes gravity out of the equation and lets acid pool in your food pipe. Eating close to bedtime makes it worse. Raising the head of your bed and leaving three hours after eating are the two changes that help most.

    Does it go away after birth?

    For most people, yes. Cleveland Clinic notes that heartburn in pregnancy usually settles once the baby is born, so if you never had reflux before pregnancy there is a good chance you will not have it afterwards.

    This article is educational and is not medical advice. Talk to your midwife, GP or another qualified healthcare provider about your own symptoms, and before taking any medicine during pregnancy.

    Featured image: “Glass of milk” by Santeri Viinamäki, CC BY-SA 4.0, via Wikimedia Commons.

    Sources

  • How to Track Ovulation Without an App: What Works

    How to Track Ovulation Without an App: What Works

    A few days in the middle of every cycle matter more than the rest, and your body marks them in advance. Reading those marks yourself is a learnable skill. Learning how to track ovulation without an app comes down to four signals: cervical mucus, basal body temperature, LH test strips, and the pattern of your own cycle. Each of them has limits worth knowing before you trust it.

    Key takeaways

    • Ovulation usually happens about 14 days before your next period, not automatically on day 14 of the cycle.
    • Cervical mucus that turns clear, wet and stretchy is the most useful signal you can read at home.
    • Basal body temperature confirms that ovulation happened; it cannot tell you it is about to.
    • Calendar maths is the weakest method, and a 2026 analysis of 543,167 cycles found it marked at least one fertile day as safe in 67% of them.
    • Most people need three or more charted cycles before their own pattern becomes readable.

    What ovulation is, and why the day-14 rule fails

    Ovulation is the moment a mature egg leaves your ovary. On average it lands around day 14 of a 28-day cycle, counting the first day of bleeding as day 1. A normal cycle runs anywhere from 21 to 35 days, so your ovulation day moves with it. The egg itself survives roughly 12 to 24 hours after release.

    Sperm live longer inside the uterus, usually three to five days. That mismatch is why the fertile window is wider than ovulation itself. Sex can lead to pregnancy from about five days before ovulation to one day after. Ovulation is only one phase of the cycle, and the rest of the month has its own cues, from appetite and energy through to the dip before your period.

    How to track ovulation at home, signal by signal

    Cervical mucus

    Cervical mucus changes texture as oestrogen climbs before ovulation. It usually moves from dry or tacky, to sticky, to creamy, and finally to something slippery that looks like raw egg white. That last stage lasts about three or four days and is the most fertile stretch of the cycle. This is where most people start when they learn how to track ovulation at home.

    A rough pattern to compare against:

    • Dry or sticky, like paste, often white or light yellow
    • Creamy, smooth and white, a bit like yoghurt
    • Wet, watery and clear
    • Slippery, stretchy and clear, close to raw egg white

    Chart it for at least two cycles before reading much into it. Several things blur the reading, including feminine hygiene products, douching, recent sex, breastfeeding, and lubricant used during a pelvic exam. If you keep a private cycle record, note the mucus texture next to the date so the pattern shows up on paper. If your mucus never seems to reach the slippery stage, that is worth raising with a doctor rather than guessing at.

    Basal body temperature

    Basal body temperature is your temperature at complete rest, taken before you get out of bed. After ovulation, progesterone nudges it up by roughly 0.5 to 1 degree Fahrenheit, and it stays higher until your next period. The catch is direction. A rise confirms that you ovulated, not that you are about to.

    ACOG puts your most fertile days at the two or three days before that shift appears. If you are learning how to track ovulation, treat the thermometer as a confirmation tool rather than a forecast. Chart for at least three cycles, because a single cycle is mostly noise.

    Fever, alcohol, poor sleep, stress, travel across time zones and some medicines all push the number around. An irregular cycle makes the method unreliable. A thermometer used after you have been up and moving is not measuring basal temperature at all.

    LH test strips

    Ovulation test strips detect luteinising hormone in your urine. The LH surge arrives before the egg is released, so a positive result usually means ovulation within about 36 hours. Cleveland Clinic suggests testing in the morning and starting around day 10 of your cycle, then continuing until you get a positive.

    Test strips are the only one of these four signals that looks forward instead of back. The trade-off is cost and waste, because a strip used on a quiet day tells you nothing new. A large 2026 study used urine LH tests as its reference standard precisely because they sit closest to the biology.

    Cycle arithmetic

    The oldest approach to how to track ovulation is arithmetic. Ovulation tends to arrive about 14 days before your next period, so a 30-day cycle points to roughly day 16. That estimate weakens the more your cycle length varies, and it is the method the 2026 analysis found most error-prone. Stress and illness can also push ovulation back by a few days, which is why a stress-shifted cycle breaks predictions made months in advance.

    Keep a simple record of the first day of each period for several months. A paper diary or a wall calendar does the job. What you are looking for is your own average, not the textbook one.

    What the evidence says about getting it wrong

    Two separate bodies of evidence should temper anyone’s confidence. NHS guidance puts fertility awareness at 91 to 99 percent effective with perfect use for contraception, and only 76 percent with typical use, which works out to 24 pregnancies per 100 women over a year. ACOG’s figures are in the same territory, with 12 to 24 pregnancies per 100 in the first year of typical use.

    A 2026 observational analysis went further and checked where apps actually go wrong across 543,167 cycles. Calendar-based tracking put at least one genuinely fertile day in the safe zone in 67 percent of cycles, with a predicted pregnancy risk of 22 percent. BBT-supported tracking did better but still missed in 41 percent of cycles, with a risk of 9 percent. A regulated digital contraceptive, cleared as a medical device, came in at 3 percent.

    The conclusion is narrow but firm. Period trackers misclassify fertile days often enough that they should not be used to prevent pregnancy. For people with irregular cycles the calendar-based numbers were worse still, reaching a 65 percent risk.

    When to see a doctor

    Occasional twinges around ovulation are common and usually harmless. Ovulation pain typically lasts from a few minutes to a day or two and tends to switch sides from cycle to cycle. Get medical advice if the pain is severe, does not ease with painkillers, keeps coming back, or arrives with a fever, unusual discharge or bleeding between periods.

    You may not be ovulating at all if you go months without a period. Thyroid problems, primary ovarian insufficiency, very high exercise loads and significant stress can all be behind it. Irregular or absent cycles are worth investigating rather than tracking harder, and the cycle and fertility archive collects more on the signals worth raising with a doctor.

    How Lail can help

    Lail is our own period and ovulation tracker, built for people who would rather their cycle data stayed on their phone. It estimates your ovulation day and fertile window from the cycles you log, and shows which phase you are in today. You can record symptoms, moods and weight alongside your periods, with no account required and no cloud backup. Everything sits in an encrypted database on the device, and you can find it on Google Play alongside the rest of our tools on the products page.

    FAQ

    Can I track ovulation using only my period dates?

    You can estimate it, but estimates built from period dates alone are the least reliable option. They assume ovulation sits a fixed number of days before your next period, which only holds for regular cycles. The 2026 analysis found this approach marked fertile days as safe in two-thirds of all cycles.

    How accurate is cervical mucus on its own?

    It is one of the better at-home signals, though it is a pattern rather than a switch. Expect the slippery stage to last about three or four days before ovulation. Medicines, hygiene products and recent sex can all muddy the reading.

    Do I need to chart all four signals at once?

    Most people find two or three is enough, and mucus plus cycle maths is the lightest starting point. Adding basal body temperature gives you confirmation after the fact. Reading all four at once gets tedious fast and tends to fall apart by the second month.

    How many cycles should I chart before trusting the pattern?

    Three is a reasonable minimum for basal body temperature, and two for cervical mucus. Charting longer gives you a better sense of how much your own cycle moves around. If you are tracking to conceive and the picture stays unclear, raise it with a doctor rather than charting for another year.

    This article is educational and is not medical advice. Talk to a qualified healthcare provider about your own cycle, fertility or contraception.

    Featured image: Open calendar with scribbled notes, rawpixel, CC0 1.0, via Openverse

    Sources

  • Braxton Hicks vs Real Contractions: How to Tell the Difference

    Braxton Hicks vs Real Contractions: How to Tell the Difference

    Halfway through the third trimester, your bump tightens into a hard ball and holds there for a moment before it softens again. You can still talk through it, and you can still walk, but twenty minutes later it happens again. This is where most people start searching braxton hicks vs real contractions, because the two can feel surprisingly similar until you know what separates them. A few concrete differences, and the habit of watching the clock, usually make the answer obvious.

    Key takeaways

    • Braxton Hicks contractions are normal practice tightenings, and they do not open the cervix.
    • The clearest signal in braxton hicks vs real contractions is the trend: practice tightenings wander, true labor builds.
    • True labor contractions settle into a rhythm and get closer together over time.
    • Rest, water and a change of position often quiet Braxton Hicks, but they will not stop real labor.
    • Call your midwife or maternity unit if your waters break, you bleed, your baby moves less than usual, or a contraction lasts longer than two minutes.

    What Braxton Hicks contractions are

    Braxton Hicks are the tightenings your uterus makes as it prepares for birth. Cleveland Clinic calls them practice contractions, and notes they can begin as early as the second trimester, though plenty of people never notice them at all. They often feel like mild period cramps or a band of tightness across the belly, and they are usually strongest at the end of the day. NHS guidance describes them as uncomfortable but normally painless, and adds that they do not last long, do not come often and do not build up.

    When they start, and what they do not mean

    Nobody knows exactly why some people get Braxton Hicks and others do not. What providers do know is that they happen when the uterus is getting ready for labor, and some think they help soften and thin the cervix along the way. The important part is what they do not do. They do not open the cervix, they do not fall into a regular pattern, and they are not a sign that labor is starting.

    Braxton Hicks vs real contractions: the four differences that matter

    Timing, strength, how they respond to movement and where you feel them are the four things that separate one from the other. Put together, the differences in braxton hicks vs real contractions come down to four practical questions. Here is how ACOG and Cleveland Clinic answer each one.

    • Real contractions arrive at regular intervals and the gaps between them get shorter, while Braxton Hicks stay irregular and never settle into a rhythm.
    • Real contractions build steadily and become hard to talk through, while Braxton Hicks vary in intensity but do not keep escalating.
    • Walking, resting or changing position tends to ease Braxton Hicks, while real contractions carry on regardless.
    • Labor pain usually starts low in the back and spreads to the front, while Braxton Hicks are generally felt only at the front of the belly.

    A single symptom on its own proves little. ACOG notes that the only certain way to confirm true labor is a vaginal exam showing the cervix changing, which is why your midwife will ask about the overall pattern rather than one contraction.

    How to time contractions

    Timing turns a vague ache into useful information, and it is the one thing you can do at home. Note when a contraction starts, when it ends, and the gap until the next one, then watch how those numbers change over an hour or two. ACOG suggests noting whether the contractions continue while you rest and drink water, because false ones often fade with both. That is what makes braxton hicks vs real contractions a question most people can answer themselves: a true pattern tightens and shortens the gaps, while a false one drifts.

    What triggers Braxton Hicks, and what helps

    Cleveland Clinic lists dehydration, heavy activity, a full bladder, sex and lifting as common triggers. When one starts, drink a glass of water, empty your bladder, change position and give it a few minutes. Most settle on their own, and they are not a sign that anything is wrong. If they keep coming in a steady rhythm despite rest, treat that as a reason to call your midwife rather than a reason to wait.

    The blurry start of real labor

    Real labor usually begins with a long, untidy stretch before anything looks like the movies. NHS guidance calls this the latent phase, and it can last hours or occasionally days while the cervix softens and starts to open. During this time you will often be advised to stay at home, and if you go to the hospital early you may be sent home again. The practical job is to rest, eat, drink and keep timing, rather than to rush anywhere.

    When to call your midwife or maternity unit

    NHS guidance is direct: call your midwife or maternity unit if you think you are in labor, or if your contractions are coming every five minutes or more often. Call urgently if your waters break, you have vaginal bleeding, your baby is moving less than usual, you are less than 37 weeks pregnant and think labor has started, any contraction lasts longer than two minutes, or you have six or more contractions in ten minutes. ACOG adds that you should go to hospital if your waters have broken and you are not contracting, if you are bleeding heavily, or if you have constant severe pain with no relief between contractions. If you feel a strong urge to push and think your baby is coming now, call 999, and remember that being unsure is a good enough reason to ring.

    If you are checking your baby’s movements as well, our guide to kick counting explains how to build a clear daily picture. Lower back pain with no rhythm behind it is usually a separate late-pregnancy ache rather than labor, and our piece on back pain during pregnancy covers what tends to help. The rest of our pregnancy health guides are in one place too.

    How Utun can help

    Utun is our own pregnancy companion app, built around the practical side of late pregnancy. It includes a contraction timer that records how long each contraction lasts and how far apart they are, so you can watch the pattern instead of guessing at it. There is also a kick counter for tracking your baby’s movements, a mood journal, a hospital bag checklist and trimester to-do lists. You can download it on the Play Store and see the rest of our apps on the products page.

    FAQ

    Can Braxton Hicks contractions be painful?

    Yes, they can be. Cleveland Clinic describes them as less intense than real contractions on average, but ACOG notes they can still be painful enough to make you think labor has started. The giveaway is not the pain itself but the pattern, or the lack of one.

    How often should I feel them?

    There is no normal number. Some people feel a few a day and others notice nothing at all, and Cleveland Clinic says they can start as early as the second trimester. What matters is whether they stay irregular or begin to settle into a rhythm that gets closer together.

    Do Braxton Hicks mean labor is close?

    Not on their own. Cleveland Clinic says they are your body getting ready for labor, but they do not mean labor is coming, and they can happen for many weeks beforehand. ACOG points out that you may notice them more at the end of the day, which is normal.

    How long do real contractions last?

    ACOG puts a true labor contraction at about 60 to 90 seconds, arriving at regular intervals that get closer together. Cleveland Clinic describes them as lasting 40 to 60 seconds and becoming more frequent over time. Either way, the number matters less than the trend.

    This article is educational content and is not medical advice. Always speak to your midwife, doctor or another qualified healthcare professional about your own pregnancy and any symptoms that worry you.

    Featured image: Heart shape on a pregnant belly by freestocks.org (CC0 1.0, public domain) via Openverse.

    Sources

  • Magnesium for Period Cramps: What the Evidence Actually Shows

    Magnesium for Period Cramps: What the Evidence Actually Shows

    That kind of pain does not care about your plans. By the time the painkillers wear off, most people will try whatever is in the cupboard. So does magnesium for period cramps actually change anything, or is it a supplement with a better marketing budget than evidence? The research is small, older than you would expect, and more interesting than the internet usually admits.

    Key takeaways

    • Magnesium sits in more than 300 enzyme reactions, including the muscle and nerve functions that decide how a contraction feels.
    • The strongest evidence for painful periods comes from three small trials published in 1989 and 1990, plus one 2022 trial against the contraceptive pill.
    • A 2016 Cochrane review of 27 supplement trials rated every comparison low or very low quality, and safety reporting was close to absent.
    • The upper limit for magnesium from supplements is 350 mg a day, and diarrhoea is the usual sign you have passed it.
    • Food carries magnesium with no laxative ceiling, and pumpkin seeds, beans, nuts and leafy greens are the cheapest places to find it.

    What magnesium does in your body

    Magnesium is a mineral your body uses in more than 300 enzyme reactions: building proteins and bones, regulating blood sugar and blood pressure, and running muscle and nerve signals. Harvard’s Nutrition Source describes it as an electrical conductor that contracts muscles and keeps the heart beating steadily.

    Muscle contraction is the part that matters for monthly pain. Period pain happens when the womb tightens during your period, according to the NHS. A 2020 review in Nutrients explains magnesium’s role in pain as an antagonist at the NMDA receptor, which reduces central sensitisation and dampens an already sensitised pain system.

    Nobody has shown that low magnesium causes period pain. The mineral simply sits inside the pathways that regulate contraction and pain signalling, which is why researchers tested whether adding more of it changes the experience.

    What the evidence on magnesium for period cramps shows

    The best summary of magnesium for period cramps is still the 2001 Cochrane review by Proctor and Murphy. Three small trials compared magnesium with placebo, and overall magnesium was better for pain relief while women needed less additional medication. There was no significant difference in the number of adverse effects. The reviewers called magnesium promising, but said the dose and schedule could not be pinned down from the trials available.

    Two of those trials are worth knowing in detail. Seifert and colleagues followed 50 women with primary dysmenorrhoea for six months in a double-blind study: 21 of the 25 women on magnesium reported fewer symptoms, and prostaglandin F2 alpha in menstrual blood fell to 45% of the pre-treatment level, against 90% in the placebo group. Fontana-Klaiber and Hogg ran a smaller double-blind trial of 32 women and analysed 21 of them. Magnesium did little on day one, helped back pain and lower abdominal pain on days two and three, and cut days lost from work.

    Newer evidence is thinner than the supplement aisle suggests. A 2022 study followed 172 women with primary dysmenorrhoea for three cycles: 86 took 200 mg of magnesium citrate daily and 86 took a combined oral contraceptive. The magnesium group finished with significantly lower pain scores than before treatment and needed fewer painkillers, but the contraceptive group did better on both measures. That study had no placebo arm.

    A 2020 meta-analysis of micronutrients in primary dysmenorrhoea screened 16 clinical trials and listed magnesium among the supplements with a desirable effect on pain. Only six studies were pooled, though, and the pooled results that reached significance were for vitamin D and vitamin E, not magnesium.

    The honest counterweight for anyone weighing magnesium for period cramps is the 2016 Cochrane review of dietary supplements for period pain. It covered 27 trials and 3,101 women, mostly students in their late teens and early twenties in Iran, and graded every comparison as low or very low quality. Only four of the 27 trials reported adverse effects in both treatment groups. Magnesium was not among the supplements included in that update, so the 2001 conclusion remains the fairest reading: promising, tiny, and unclear on dose.

    One more finding is worth flagging for anyone whose symptoms run into the week before their period. A 2017 systematic review of 14 trials found that magnesium combined with vitamin B6 reduced premenstrual anxiety, but magnesium on its own did not, and neither version changed stress levels in women with dysmenorrhoea.

    Which type of magnesium, and how much

    Supplements come as magnesium oxide, hydroxide, gluconate, chloride and citrate salts, plus amino acid chelates such as magnesium aspartate. A few of those salts are also used as antacids and laxatives, which tells you something about how they behave in the gut. No trial has compared the forms head to head for cramps, and the studies that did show a benefit used different preparations: a granulate in 1990, 200 mg of citrate daily in 2022. The practical answer for magnesium for period cramps is to pick a form you tolerate and can take consistently.

    The dose ceiling is better documented than the dose target. The tolerable upper intake level for magnesium is 350 mg a day from supplements only, and it exists specifically because higher intakes cause diarrhoea and gastrointestinal upset. That limit does not apply to magnesium from food, because the kidneys clear the excess.

    Magnesium also interferes with some medicines. It reduces the absorption of digoxin, nitrofurantoin and certain antimalarials, needs a two-hour gap from bisphosphonates such as alendronate, and can reduce the effect of chlorpromazine, penicillamine, oral anticoagulants and quinolone antibiotics. If you take prescription medicine daily, ask a pharmacist before adding a supplement.

    Food sources first

    About 30% to 40% of the magnesium you eat is absorbed, and absorption shifts with the amount eaten and with the rest of the meal. Adults need 310 to 320 mg a day, more during pregnancy. Good sources, according to MedlinePlus and Harvard, include:

    • Pumpkin seeds, almonds, cashews, peanuts and hazelnuts.
    • Beans, peas, lentils, chickpeas and soy products such as tofu.
    • Leafy greens such as spinach, whole grains such as brown rice, avocados and bananas.
    • Milk, and fortified foods such as breakfast cereals.

    A bowl of beans and a handful of seeds gets you a long way toward the daily figure without touching the supplement ceiling. If your diet is already built on those foods, the case for a pill gets weaker.

    What else helps with cramps

    The NHS self-care list is unglamorous and better evidenced than any supplement: a warm bath or shower, a heat pad or hot water bottle wrapped in a tea towel on your tummy, massage, and gentle exercise such as yoga, swimming, walking or cycling. Paracetamol and ibuprofen are listed as first-line painkillers, and ibuprofen specifically lowers the prostaglandins behind the contractions.

    Three articles on this site go deeper on those options. Our piece on heat for period cramps covers the head-to-head trials, ginger and chamomile tea looks at the herbal evidence and its limits, and what to eat on your period maps food to each phase of the cycle. For more in this cluster, browse the Cycle & Fertility archive.

    When to talk to a doctor

    Period pain that is severe or worse than usual and has not eased with painkillers needs an urgent appointment or a call to NHS 111. Book a routine appointment if your periods are getting heavier or more painful, if pain stops you doing your usual activities, if sex or going to the toilet hurts, if you bleed between periods, or if you have a swollen tummy, no appetite or unexplained weight loss. Skip magnesium supplements until you have spoken to a doctor if you have kidney problems, because impaired kidney function raises the risk of a build-up.

    How Lail can help

    Lail is our own period tracker for Android, and it keeps everything on your phone rather than in a cloud account. You can log symptoms, mood, flow and weight, and see insights built around each phase of your cycle, which is how you find out whether the magnesium, the heat pad or the earlier bedtime actually changed anything. There is no account and no cloud backup; the database is encrypted on your device. You can download Lail from the Play Store or find it alongside our other apps on the products page.

    How long does magnesium take to work for period cramps?

    The trials that showed a benefit dosed across whole cycles rather than single days. The 1990 study gave magnesium the day before bleeding plus days one and two, while the 2022 study measured pain after three cycles. Give magnesium for period cramps two full cycles before you judge it.

    Which magnesium is best for period cramps?

    No trial has compared the forms against each other for cramps, so any confident ranking online is guesswork. Trials have used a granulate and magnesium citrate, and the safety limit of 350 mg a day applies to all of them. Choose one you tolerate and keep the total below that ceiling.

    Should I take magnesium every day or only during my period?

    Both approaches have been tested, and neither has been compared with the other. The 1989 trial dosed continuously for six months, while the 1990 trial used a short window around bleeding. Daily dosing is easier to remember; the trade-off is more days of loose stools if you overshoot the dose.

    Can magnesium replace painkillers?

    No. In the 2022 trial the contraceptive pill outperformed magnesium, and the NHS still lists paracetamol and ibuprofen as first-line treatment. Treat magnesium as an addition to your usual pain plan, not a replacement for it.

    This article is educational and is not medical advice. Talk to a qualified healthcare provider about your own symptoms, medicines and supplements.

    Featured image: Roasted Pumpkin Seeds by jaxzin via Flickr (CC BY 2.0).

    Sources

  • Metallic Taste in Mouth During Pregnancy: Causes and Relief

    Metallic Taste in Mouth During Pregnancy: Causes and Relief

    Water tastes faintly of coins, coffee that was once a small pleasure now smells off, and the aftertaste of a plain meal lingers for hours. It sounds odd, but it is one of the stranger symptoms of the first few months, and it often arrives alongside nausea. A metallic taste in mouth during pregnancy is common enough that clinicians have a name for it: dysgeusia. It usually fades on its own, and there are practical ways to make eating less of a chore until it does. If you are keeping track of early symptoms, frequent urination in early pregnancy is another one that tends to show up early.

    Key takeaways

    • Dysgeusia is the medical term for a distorted sense of taste, and it is common in early pregnancy.
    • Hormone shifts are the usual explanation, and smell matters as much as your taste buds do.
    • It usually settles after the first trimester, though not always on a fixed schedule.
    • Citrus, sour foods, cold meals and non-metal cutlery are the changes most likely to help at the table.
    • Speak to your midwife or GP if you cannot keep food or fluids down, or you are losing weight.

    What dysgeusia actually is

    Dysgeusia is a taste disorder in which food stops tasting the way it should. Everything seems metallic, bitter, sour or rancid, and a foul taste can sit in your mouth even when you have eaten nothing. Cleveland Clinic notes that up to 17% of people in the United States experience it at some point, and it can flatten your appetite.

    Taste is not only about the tongue. Cleveland Clinic reports that smell accounts for about 80% of what you perceive as flavour. A blocked or newly sensitive nose can therefore make a familiar dish taste completely different.

    What causes a metallic taste in mouth during pregnancy

    The most widely repeated explanation for a metallic taste in mouth during pregnancy is the hormone surge of the first trimester. Cleveland Clinic states that dysgeusia in pregnancy is common and usually due to a surge of hormones, and that it typically goes away on its own after the first trimester. A 2010 review in Chemosensory Perception by Marijke Faas and colleagues describes how estrogen and progesterone affect food intake and taste, which fits the timing.

    The story is messier than “hormones did it”. A 2017 review in Chemical Senses by Elizabeth Choo and Robin Dando looked at studies measuring taste thresholds rather than self-reports, and found the results inconsistent. Most reported either no change in pregnancy or a drop in perceived taste intensity, especially early on. That suggests taste acuity may fall rather than sharpen.

    Choo and Dando also note that taste buds carry receptors for many of the same hormones that shift during pregnancy, and argue the effect is not driven by progesterone and estrogen alone.

    Three ordinary things can pile on top of the hormonal picture. A dry mouth concentrates whatever is already in your saliva, and acid reflux puts stomach contents back where your taste buds can reach them; Cleveland Clinic lists both as causes of altered taste. If that reflux is also burning at night, heartburn in pregnancy has the practical fixes.

    Morning sickness adds to the mix. A 2025 review in Evolution, Medicine, and Public Health by David Stadtmauer identifies the placental hormone GDF15 as a principal causal factor in pregnancy sickness, with around 1% of cases progressing to hyperemesis gravidarum.

    Why food also tastes bitter or simply wrong

    Bitter is the other complaint that comes up constantly in early pregnancy, and it tends to arrive in the same weeks as nausea. Coffee, green vegetables and dark chocolate are the usual casualties, while sweet foods often lose their pull. The 2017 Chemical Senses review names this pattern directly: an increased bitter response and a decreased sweet response are the changes women most often report.

    Whether that reflects a real change in your taste receptors or in how much you notice certain flavours is still debated. If your nose has turned against perfumes and cooking smells too, our guide to smell sensitivity during pregnancy explains what is happening there.

    How long does a metallic taste in mouth during pregnancy last?

    For most women it is a first-trimester event. Cleveland Clinic says symptoms typically resolve on their own after the first trimester, and NHS guidance on morning sickness notes that nausea and vomiting usually clear by weeks 16 to 20 of pregnancy.

    The research itself is not settled: the Chemical Senses review found that studies disagree, and several measured no change at all. If taste changes still dominate your meals at 20 weeks, raise it at an antenatal appointment.

    What helps when everything tastes of metal

    Start with the food itself. Cleveland Clinic advises eating foods that mask a metallic taste in mouth during pregnancy, naming citrus fruit, sour foods such as pickles, and anything made with vinegar. It also suggests cutting back on heavily spiced, very sweet or preservative-heavy dishes.

    Temperature and timing are worth experimenting with. Cold or room-temperature food releases fewer aromas than a hot meal, so a chilled plate or a cold sandwich can be easier to face than a hot version. Small, frequent snacks tend to beat three full meals, and plain carbohydrate-heavy food is usually the least offensive. NHS guidance recommends small, frequent meals of plain, high-carbohydrate, low-fat food, plus something dry such as toast before you get up.

    Then deal with the metal in your mouth rather than the food on the plate. Cleveland Clinic suggests swapping metal cutlery and metal water bottles for glass, plastic or ceramic ones. Sucking on ice cubes or sugar-free ice pops keeps your mouth from going dry, and brushing, flossing and rinsing after meals is recommended as well.

    Sipping water through the day is the simplest lever, because a dry mouth makes a distorted taste worse, and non-caffeinated drinks count towards it. When you want more flavour, the National Institute of Dental and Craniofacial Research suggests condiments, spices and sauces rather than extra sugar or salt. It also advises avoiding mixed dishes such as casseroles, which blend everything into one flat taste.

    Supplements, myths and the boy-or-girl question

    Zinc and B vitamins genuinely matter for taste. Cleveland Clinic notes that people with zinc or vitamin B deficiencies are especially prone to dysgeusia. That does not mean a supplement will fix pregnancy-related taste changes, and there is no reliable evidence that it will. Check any new supplement with your midwife, GP or pharmacist first, the same caution NHS gives for ginger in pregnancy.

    One popular theory deserves a straight answer: a metallic taste cannot tell you whether you are having a boy or a girl. Your baby’s sex is set by chromosomes, and the reliable ways to find out are an ultrasound scan or a blood test. Tracking taste changes is worth doing for your own comfort, and nothing more.

    When to see a doctor

    A distorted sense of taste on its own is not dangerous. What matters is whether you are still getting enough food and fluid, because the combination of nausea and taste changes is what pushes some women towards dehydration and weight loss. NHS guidance treats those as the warning signs to act on.

    NHS advises contacting your midwife, GP or 111 if you are vomiting and any of the following apply: your urine is very dark or you have not passed urine in more than eight hours, you cannot keep food or fluids down for 24 hours, you feel very weak, dizzy or faint when standing up, you have tummy pain or a high temperature, you are vomiting blood, or you have lost weight.

    Ask for advice as well if the taste change comes with a persistent dry mouth, a sore or swollen tongue, or anything else that does not fit the usual early-pregnancy pattern. A clinician can check for other causes on Cleveland Clinic’s list, including infection, reflux, medication effects and vitamin or mineral deficiencies. You can find more symptom guides on our pregnancy health hub.

    How Utun can help

    Utun is a pregnancy companion app for Android. It gives you development information with daily guidance matched to how far along you are. It also has a health tracker with a weight log, a kick counter and a contraction timer, plus a mood journal, a hospital bag checklist and trimester to-do lists. Utun is on the landing page and on Google Play.

    Is a metallic taste an early sign of pregnancy?

    It can be, though it is not one of the classic early signs such as a missed period or nausea. Cleveland Clinic describes a metallic taste in mouth during pregnancy as common and tied to the hormone surge of early pregnancy. A pregnancy test taken after a missed period will tell you far more than your taste buds will.

    Why does water taste bitter or metallic?

    Water has almost no flavour of its own, so it is the easiest thing in your day to notice a change in. Saliva, a dry mouth and shifting hormones all affect how things register, and plain water is the least masked of all drinks. Adding a squeeze of lemon or drinking it cold often makes it drinkable again.

    Does it mean something is wrong with my baby?

    There is no evidence that a metallic or bitter taste is a sign of a problem with your baby. What does need attention is how much you are eating and drinking, because ongoing sickness can lead to dehydration and weight loss. Call your midwife, GP or 111 if you cannot keep fluids down or your urine is very dark.

    Can I take zinc supplements for it?

    Not without asking a clinician first. Zinc deficiency is associated with taste problems, but there is no reliable evidence that taking zinc resolves pregnancy-related taste changes. Your midwife, GP or pharmacist can advise on whether any supplement is appropriate for you.

    This article is educational and is not medical advice. Always speak to your midwife, GP or another qualified healthcare professional about your own pregnancy.

    Featured image: “Sliced Lemon” by Studio 7042, used under CC0 1.0 via StockSnap.

    Sources

  • Exercises to Avoid During Your Period, and What to Do Instead

    Exercises to Avoid During Your Period, and What to Do Instead

    Day three, and the plan on your phone says heavy squats. Your body has filed a complaint. Training advice tends to swing between “push through it” and “stay in bed,” which leaves the boring middle unanswered. That middle is where the honest answer to which exercises to avoid during your period actually lives.

    Key takeaways

    • Periods are not a medical reason to stop training, and NHS guidance lists gentle movement such as walking, swimming, cycling and yoga among its pain-relief steps.
    • The exercises to avoid during your period are the ones that spike your own symptoms: max-effort lifts, high-impact jumping, and long sessions in the heat.
    • Heavy bleeding plus a hard training block is the combination most likely to drain your iron stores.
    • A period that disappears while you train hard is a signal to get checked, not a badge of discipline.
    • Stop mid-session if you feel faint, dizzy or flood through a pad in an hour, because those belong in a doctor’s office rather than a grit test.

    What the research says about training on your period

    Clinicians do not treat menstruation as a reason to stop moving. Cleveland Clinic notes that people who exercise tend to have less menstrual pain, and NHS period pain guidance names gentle exercise such as walking, swimming, cycling and yoga among its self-care steps. A 2024 Bayesian network meta-analysis of 33 randomised trials in BMJ Evidence-Based Medicine put exercise at roughly a three-point drop in pain intensity on a ten-point scale. The same review hedges, describing non-drug options as things that “may result in a reduction or slight reduction in pain intensity” and calling for larger trials.

    The research is friendly, but it describes averages rather than your Tuesday. What shifts across a period is tolerance, not permission. Cramping happens when prostaglandin makes the uterus contract, and levels are highest around the start of bleeding, which is when the same workout can feel twice as heavy. Cleveland Clinic estimates that about 60% of people who menstruate get mild cramps, while 5% to 15% report pain severe enough to interfere with daily activities.

    Exercises to avoid during your period

    There is no medical list of banned movements, so treat any confident version of one with suspicion. In practice, the exercises to avoid during your period are the ones that make your own symptoms worse, and for most people that means changing the dose instead of cancelling the session. Here is where the adjustments usually land.

    Max-effort lifting is the first thing to scale back. A one-rep-max deadlift or a session built on hard bracing asks for stamina and a steady core rhythm, and both are harder to hold on your heaviest days. High-impact work comes second: box jumps, sprint intervals and long downhill runs land hard when your pelvis already aches. Long sessions in the heat, hot yoga included, get rough fast when you are already lightheaded.

    Yoga inversions deserve their own note. The rule that going upside down sends menstrual blood the wrong way is studio folklore, and NHS guidance does not single out any pose as one to stop. If inversions feel fine they are fine, and if they make you dizzy, that is the whole reason to skip them.

    Anything a doctor has flagged outranks all of this. Endometriosis, a bleeding disorder, a history of anaemia or a heart condition each change the picture, and your clinician’s advice wins. Swimming is the classic case of an exercise people avoid for cultural reasons rather than medical ones, and NHS guidance names it as a way to ease period pain.

    Why heavy bleeding and hard training are a poor pairing

    Iron is where period training most often goes wrong. NHS says iron deficiency anaemia is usually caused by blood loss, and lists tiredness, shortness of breath, palpitations, pale skin and headaches among the signs. A 2018 review in the European Journal of Sport Science found that menstruating athletes, particularly those with heavy menstrual bleeding, carry a higher risk of iron deficiency. That matters twice in training, because iron carries the oxygen your muscles keep asking for.

    Heavy bleeding has a working definition, and it helps to know where you sit. NHS counts changing a pad or tampon every one to two hours, using two products at once, periods longer than seven days, or clots bigger than about 2.5cm. A study of 30 female varsity athletes in Applied Physiology, Nutrition, and Metabolism found 20% were iron deficient, and that a higher menstrual loss score went with lower ferritin. If your flow is heavy and your training block is heavy, ask for a ferritin test instead of guessing.

    Can training too much change your cycle?

    Yes, and this is the part of the question where the risk is real and well documented. NHS lists “doing too much exercise” among the common causes of missed or late periods, alongside sudden weight loss and stress. Sports medicine describes the same pattern through low energy availability: burn more than you take in for long enough and the hormonal signal driving your cycle weakens. A 2019 review in Sports Medicine sets out how that plays out across menstrual function and bone health, and notes there is no single energy threshold where it starts.

    The distinction that matters is sustained under-fuelling against one hard day. A brutal session on day two will not stop your period, but months of eating too little around hard training can. A 2026 narrative review in Frontiers in Sports and Active Living, drawing on 151 studies, describes menstrual dysfunction as a clinical barometer of energy deficiency and links it to weaker bone density over time. Missing periods has plenty of other causes, so treat it as a reason for a check-up rather than a self-diagnosis.

    What to do on the days you feel awful

    Scale intensity and keep the habit. A twenty-minute walk, an easy spin, a swim or a mobility session keeps your routine intact and often eases cramps. NHS self-care for period pain also covers a heat pad wrapped in a tea towel, a warm bath, and painkillers such as paracetamol or ibuprofen. If you need painkillers to get through training most months, book a GP appointment rather than buying another supplement.

    Move the hard sessions when your schedule allows. For a lot of people the first two days are the worst and things ease after that, so the heaviest lifting can wait a week or two. There is no rule that your training week has to look identical seven days out of seven.

    When to see a doctor

    Get urgent help if period pain is severe or worse than usual and painkillers have not touched it, or if you feel faint during or after training. Book a GP appointment if heavy periods are affecting your life, you bleed between periods, your periods run past seven days, or you have missed three in a row. Unusual breathlessness, palpitations and fatigue during exercise are worth mentioning too, since they can point to anaemia. None of that is a failure of effort.

    How Lail can help

    Tracking is the unglamorous half of this problem. Lail is a private period tracker for Android that keeps your data on your phone, with no account and no cloud sync. You can log flow, cramps, mood and weight, then look back at which days your training actually fell apart. That record does more at a GP appointment than a vague memory of a bad month, and you can install Lail from Google Play.

    This article is educational and is not medical advice. Talk to a qualified healthcare professional about your own symptoms and before changing how you train.

    Featured image: a woman holding a push-up position on a mat. Photo by homegets.com on Flickr, CC BY 2.0: https://www.flickr.com/photos/141436406@N04/49778014313

    FAQ

    Is it safe to lift weights on my period?

    For most people, yes. Strength training does not appear on any medical no-go list for menstruation. What changes is how much you can recover from, so save the one-rep-max attempts for a week when you feel less flat.

    Should I skip the gym on my heaviest day?

    Not automatically. If your flow is heavy and you feel drained, an easy session beats a hard one, but no medical rule says stay home. Adjust the plan instead of dropping the habit.

    Does exercise make period pain worse?

    The evidence points the other way. The 2024 network meta-analysis found exercise reduced pain intensity, and NHS lists gentle exercise among its self-care advice. If your experience differs, track it for two or three cycles before deciding.

    Which exercises to avoid during your period should I genuinely skip?

    Only the ones that make your symptoms worse on the day. The exercises to avoid during your period are the ones that spike pain, not a fixed list you have to memorise. Everything else stays optional.

    Can too much exercise stop your period?

    It can be one cause, and NHS lists it among the common reasons periods go missing. The mechanism is usually sustained low energy availability rather than the workout itself. If you have missed three periods in a row, see a GP.

    Sources

  • Smell Sensitivity During Pregnancy: Causes and Relief

    Smell Sensitivity During Pregnancy: Causes and Relief

    One morning the coffee that has started your day for a decade smells like something burning, and the thought of it is enough to drive you out of the kitchen. Food aversions often arrive before anyone else knows you are expecting, and their intensity can feel wildly out of proportion to what is actually happening. So when people describe smell sensitivity during pregnancy as a kind of superpower, it is worth separating what you feel from what researchers have actually measured, because the two do not line up neatly. The experience is real and very common, and there is a lot you can do about it. Taste can shift in early pregnancy too, which is why a metallic taste in your mouth often shows up in the same weeks.

    Key takeaways

    • Up to 80% of people who are pregnant get nausea, and smells are one of the most common triggers.
    • A 2022 meta-analysis of 13 studies found pregnant women did not have lower odor detection thresholds than non-pregnant women.
    • The same analysis found pregnant women were worse, not better, at identifying odors.
    • Hormones, especially hCG and progesterone, are the suspected culprits, and symptoms usually peak between weeks 8 and 10.
    • What holds up in practice: avoid strong odors, eat cold or bland food, snack often, and try ginger or acupressure.

    Why smell sensitivity during pregnancy is real

    Nobody has pinned down the exact mechanism. Cleveland Clinic reports that doctors suspect surging human chorionic gonadotropin (hCG) and progesterone, the same hormones that climb steeply in early pregnancy. The NHS puts it more simply: hormonal changes in the first 12 weeks are probably one of the causes of morning sickness.

    The timing backs that up. Nausea usually builds between weeks 8 and 10 and eases by around week 16, which tracks the hormone curve of early pregnancy. That curve also explains why smell sensitivity during pregnancy is worst in the first trimester, when those hormones are climbing fastest.

    Congestion plays a part too. Pregnancy rhinitis swells the lining of the nose and narrows the airway, and a 2025 controlled study of 50 women in their third trimester against 25 non-pregnant controls found the pregnant group scored lower on detection, discrimination and identification using Sniffin’ Sticks tests. About half of them had measurable olfactory disturbance, and most had not noticed it.

    Does pregnancy really sharpen your nose?

    This is where the popular story and the evidence part ways. A 2022 systematic review and meta-analysis in Chemical Senses pooled 13 studies, and nine were detailed enough to combine, covering 523 pregnant women and 365 controls.

    The result is blunt. The authors found no significant differences between pregnant and non-pregnant women in odor discrimination, detection thresholds, or hedonics, which is how pleasant or unpleasant a smell seems. What they did find, in a meta-analysis of 506 cases and 333 controls, was worse odor identification during pregnancy.

    So the honest position on smell sensitivity during pregnancy is that odor intolerance is real and common, even though the lab measurements do not show a sharper nose. It looks more like the same smells landing differently, with nausea and aversion amplifying the response, rather than a genuinely heightened sense of smell. The authors note that gap themselves, between widespread subjective reports of hypersensitivity and what objective testing shows.

    What helps when smells make you queasy

    Managing smell sensitivity during pregnancy comes down to reducing exposure rather than retraining your nose. The NHS recommends avoiding foods or smells that make you feel sick, and suggests cold foods over hot ones when the smell of a hot meal sets you off. That one change helps more than people expect, because cooking smells travel much further than the food itself.

    Eating little and often is the other big lever. An empty stomach makes nausea worse, so Cleveland Clinic suggests small meals or snacks every few hours, and keeping starchy food such as crackers on hand to soak up gastric acid. Protein-rich snacks like yogurt, nuts and cottage cheese are worth prioritizing, because they give longer-lasting relief than foods high in carbohydrate or fat.

    Four things worth trying first:

    • Eat cold or room-temperature meals when cooking smells are the problem.
    • Keep crackers or nuts nearby and snack every few hours instead of waiting for a full meal.
    • Try ginger, which the NHS says has some evidence for reducing nausea.
    • Ask your midwife or pharmacist before taking any supplement, including ginger capsules.

    A motion sickness band, or light pressure on the P6 point on the inside of your wrist, is another option the NHS lists alongside its lifestyle advice, and it costs nothing to test.

    Hydration needs its own juggling act. Dehydration makes nausea worse, but a very full stomach does not help either, so sipping little and often works better than large glasses. If your prenatal vitamin seems to be part of the problem, Cleveland Clinic suggests taking it in the evening with a small snack.

    Handling smells you cannot escape

    Some triggers are impossible to dodge, especially at work, on public transport or in someone else’s kitchen. Putting a scent you enjoy on a cotton ball gives you something else to smell, and Cleveland Clinic suggests chamomile, ginger, lemon, orange or peppermint, with the sensible caveat that any of them can backfire. Fresh air and an open window do more work than they get credit for.

    Small timing changes help as well. Brushing your teeth straight after eating can set off a gag reflex, so waiting around 30 minutes is kinder. Lying down after a meal lets stomach juices rise, which makes queasiness worse, so staying upright for a while is worth the effort.

    When to call your midwife or GP

    Ordinary smell aversion is unpleasant but not dangerous. Severe nausea and vomiting is a different matter, and roughly 1% to 3% of pregnant women develop hyperemesis gravidarum, which can cause dehydration, electrolyte imbalance and poor nutrition, and sometimes needs a hospital stay.

    Contact your midwife, GP or maternity unit if you cannot keep food or drink down for 24 hours, if you are losing weight, or if you have abdominal pain, a fever, difficulty urinating, or blood in your vomit. Dark urine that smells stronger than usual can point to dehydration. Anti-sickness medicines that are safe in pregnancy exist, so persistent symptoms are worth asking about rather than just enduring.

    A weakening or loss of smell is a different picture from sensitivity, and worth mentioning separately. Both the rhinitis study and a 2025 study of postpartum women found measurable smell loss around pregnancy, so a nose that has gone quiet deserves a conversation rather than a shrug.

    Early pregnancy brings plenty of other oddities too, from frequent urination to back pain, and they are easier to handle once you know what is behind them.

    How Utun can help

    Utun is a pregnancy companion that matches its development information and daily guidance to how far along you are, so you get advice for the stage you are actually in rather than for pregnancy in general. Its health trackers include a weight log, a kick counter and a contraction timer, and there is a mood journal for the days when nausea wears you down. See it at utunapp.nayabisa.com or get Utun on Google Play.

    FAQ

    How early does smell sensitivity start in pregnancy?

    Most people notice it in the first trimester, often before they have told anyone the news. Nausea tends to build between weeks 8 and 10 and eases by around week 16, and food aversions usually follow the same curve. Some people notice changes even earlier than that.

    Is a strong sense of smell a sign you are having a girl?

    There is no reliable evidence that smell changes predict your baby’s sex. The idea circulates widely, but the 2022 meta-analysis found no difference in detection thresholds between pregnant and non-pregnant women, never mind between pregnancies carrying boys and girls. Treat it as a fun theory rather than a test.

    Does smell sensitivity mean a healthy pregnancy?

    Smell sensitivity during pregnancy is not a sign of a healthy or unhealthy pregnancy. It is simply a common symptom of early pregnancy, and plenty of people never get nausea at all. What matters is whether you can keep fluids down and stay nourished.

    What smells should I avoid in pregnancy?

    There is no fixed list, because triggers are personal. Common ones include hot cooking smells, coffee, perfume, petrol and cigarette smoke. The NHS advice is to avoid whatever makes you feel sick, and to eat cold rather than hot food when cooking smells are the problem.

    Can I use essential oils for nausea?

    Cleveland Clinic suggests sniffing a few drops of chamomile, ginger, lemon, orange or peppermint oil on a cotton ball. Keep it to smelling rather than swallowing, and stop if a scent makes you feel worse. Ask your midwife before putting any essential oil on your skin.

    This article is educational and is not medical advice. Talk to your midwife, doctor or pharmacist about your own symptoms, and check with them before taking any supplement or medicine during pregnancy.

    Featured image: “Pregnant woman holding a plate of fresh fruits in a modern kitchen” by Shixart1985, CC BY 2.0, via Wikimedia Commons.

    Sources

  • Is Wearing a Panty Liner Every Day Bad? Myths vs Facts

    Is Wearing a Panty Liner Every Day Bad? Myths vs Facts

    Walk down the pharmacy aisle and you will find a wall of thin, whisper-light products sold on a single idea: that ordinary vaginal discharge is something to be managed, hidden and perfumed away. They are cheap and discreet, which is why so many people end up wearing one from Monday through Sunday without ever questioning it. So when readers ask whether wearing a panty liner every day is a problem, the answer turns out to be mostly reassuring. What does deserve attention is the type you choose, how long you leave it on, and whether it is quietly covering up a symptom worth checking.

    Key takeaways

    • Panty liners are built for very light days and spotting, not as a permanent fixture.
    • A systematic review of five studies found no negative effect on the vulvovaginal area from liner use between periods in healthy women.
    • A randomised trial of breathable liners worn 10 to 12 hours a day for 75 days found no rise in thrush, bacterial vaginosis or vulvar irritation.
    • Moisture and fragrance are the two things that actually cause trouble, so change liners often and skip scented ones.
    • Irritation that lasts more than a day or two, or discharge that changes smell, colour or texture, needs a doctor.

    What a panty liner is for

    Pads and liners sit on a spectrum of absorbency. A liner is the thinnest version, made to catch a few drops of spotting or discharge rather than a flow, and Cleveland Clinic describes liners as a low-maintenance option for the start or end of a period. A regular pad holds far more, and the difference matters, because a liner pressed into service on a heavy day just sits wet against your skin. If you are soaking through a regular pad in an hour or less, that is not a liner problem, and Cleveland Clinic advises seeing a healthcare provider.

    Does wearing a panty liner every day upset your vaginal flora?

    This is the question that has actually been studied, and for most healthy people the answer is no. A 2015 systematic review in the International Journal of Gynaecology and Obstetrics pooled five studies comparing women who used liners between periods with women who did not. Four of the five looked at healthy women and found no significant clinical effect on the genital tract, and the authors concluded that use of panty liners between periods does not seem to harm the vulvovaginal area.

    The fifth study is the one worth knowing about. It looked at women who already had recurrent candidiasis, a yeast infection that keeps returning, and found that liner use was associated with new episodes. That is an association in a group already prone to infection rather than proof that liners cause thrush, but it is a sensible reason to be careful if yours keep coming back.

    A randomised controlled trial published in 2012 tested the opposite worry, that liners might trap moisture and shift your flora. It followed 53 women who wore a breathable panty liner for 10 to 12 hours each day for 75 consecutive days, and compared them with 54 women who wore only their usual underwear. After 75 days there was no significant difference in positive fungal cultures, bacterial vaginosis, irritation or inflammation. Read that as a good result rather than a licence to leave one liner on all day, because the product tested was breathable.

    Where the infection worry comes from

    The idea that liners cause infections probably started somewhere reasonable. Wearing anything that holds fluid against warm skin for hours creates the conditions yeast and bacteria like, and a liner sits exactly there. The studies above tested that worry in real people and did not find the harm, but they also tested specific products under specific conditions.

    The habits around liner use matter more than the liner itself. If you wear one so you can skip changing your underwear, or you leave the same one on from breakfast until bed, moisture builds up no matter what the product is made of. So the question is not whether a panty liner every day is safe in principle, but whether you are changing it often enough for your skin.

    A much larger study makes the ranking of hygiene habits clear. Researchers followed 3,620 women across 13,517 visits in the Longitudinal Study of Vaginal Flora, and found that using pads or panty liners when not menstruating was not associated with bacterial vaginosis. Douching was, with a prevalence ratio of 1.17. If you are looking for one hygiene habit to drop, douching is the one with evidence stacked against it.

    Moisture, breathability and how often to change

    Change your liner when it feels damp against your skin. Cleveland Clinic suggests changing a pad at least every four to six hours during the day, and calls that a good habit because it lines up with how often most people visit the bathroom. The same rhythm works for a liner, even though it holds much less.

    Material matters too. Pads and liners come in synthetic blends, organic cotton and bamboo, and if your skin is sensitive, Cleveland Clinic suggests breathable materials or reusable cloth pads. Airflow is the point, because breathable fabric lets moisture evaporate instead of sitting against the vulva, which is exactly what the 2012 trial tested.

    Four habits cover most of it:

    • Change your liner whenever it feels damp, and at least every four to six hours.
    • Choose unscented, breathable liners over plastic-backed or perfumed ones.
    • Wash the outside with warm water and a mild, unperfumed soap, as the NHS advises.
    • Give your skin liner-free days, or sleep without one, so it can breathe.

    Scented liners and the freshness trap

    Fragrance is the ingredient most likely to cause a reaction. Cleveland Clinic recommends unscented menstrual products to lower the risk of rashes and allergic reactions, because scent irritates the sensitive skin around the vulva. Herbal-infused products are the same idea with a friendlier label, and essential oils near the vagina cause the same problems as synthetic fragrance. If wearing a panty liner every day is part of your routine, make it an unscented, breathable one.

    Scent also hides information you might need. A strong or unusual smell can be a sign of vaginitis, and covering it with perfume delays a diagnosis. If a liner is your answer to worrying about odour, that is worth mentioning to a doctor rather than solving with a product. For more on why fragrance is a poor fix, see our piece on scented pads and on everyday feminine wash.

    When daily liner use is worth a doctor’s visit

    Most irritation from liners settles within a day or two of stopping the product. Cleveland Clinic’s advice is to stop using scented products if you notice itchiness or irritation, and to book an appointment if symptoms do not clear.

    Discharge itself is normal. The NHS describes it as fluid that keeps the vagina clean and moist and protects it from infection, and says it is usually nothing to worry about when it is clear or white, has no strong or unpleasant smell, and comes without itching or soreness. It is often clearer, wetter and more noticeable around ovulation.

    See a GP or a sexual health clinic if your discharge changes in colour, smell or texture, if you produce more than usual, or if you also have itching, soreness or pain. Bacterial vaginosis usually brings a thin greyish-white discharge with a fishy smell and no itching, while thrush causes itching and irritation around the vulva. Both are common and both are treatable, so they are worth treating properly instead of masking.

    How Lail can help

    Lail is a private period tracker for Android that keeps your cycle, symptoms, mood and weight on your own device, with no account and no cloud backups. Discharge and comfort change across your cycle, so logging what you notice on which day turns a vague worry into a pattern you can describe to a doctor. The app’s insights also suggest foods for the phase you are in. Lail is free with ads, a premium tier of around Rp10,000 a month adds PDF export, and you can get it on Google Play.

    FAQ

    Is it bad to wear a panty liner every day?

    If your skin stays comfortable, a panty liner every day is not something the research gives you a reason to fear. The studies found no rise in infections or irritation among healthy women, including one trial that ran for 75 days. The practical rules are to change it when it feels damp, avoid fragrance, and stop if you notice itching or redness.

    Can panty liners cause a yeast infection?

    Liners are not a known cause of yeast infections. Four of the five studies in the 2015 review found no effect in healthy women, and the breathable-liner trial found no rise in fungal cultures after 75 days. The one study that did find a link involved women who already had recurrent yeast infections, so treat it as a caution for that group rather than a general warning.

    How often should I change a panty liner?

    Change it whenever it feels damp, and aim for every four to six hours during the day. That is the interval Cleveland Clinic recommends for pads, and it keeps moisture and odour from building up. If a liner is soaked through within an hour, step up to a higher absorbency product and mention the bleeding to a doctor.

    Do I have to wear a liner for discharge?

    No. Normal discharge is a sign that your vagina is cleaning itself, and the NHS makes clear that you cannot prevent it and usually do not need to. A liner is a comfort choice for days when discharge feels heavy or inconvenient, not a hygiene requirement.

    This article is educational and is not medical advice. Talk to a doctor or pharmacist about your own symptoms, and check with them before changing how you manage your cycle.

    Featured image: “Pantiliner” by Saibo, CC BY-SA 3.0, via Wikimedia Commons.

    Sources








